
Understanding Sarcopenic Obesity
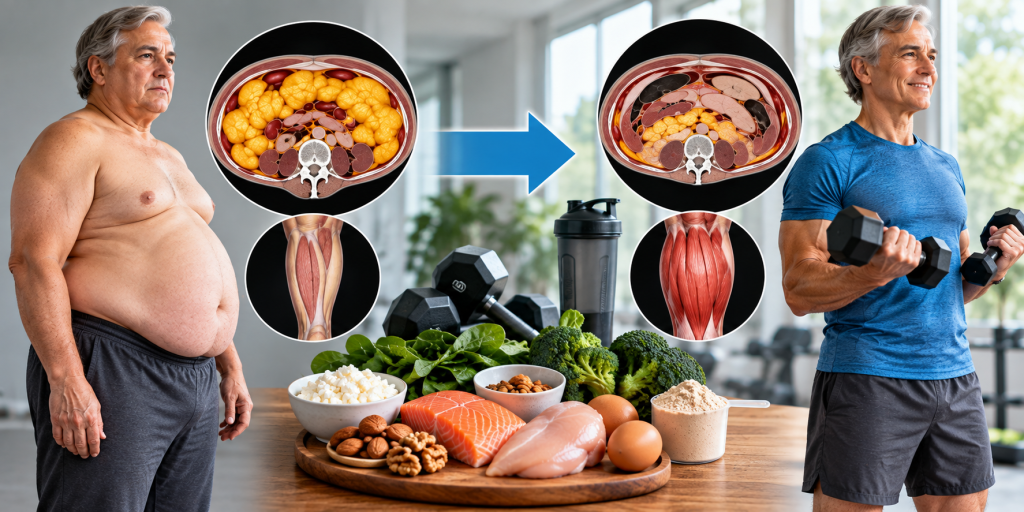
Sarcopenic obesity describes the coexistence of excess adiposity and impaired skeletal muscle health. Rather than focusing only on body weight or BMI, this condition highlights the importance of body composition, muscle strength, physical function, and metabolic health.
A person can have obesity while simultaneously having relatively low muscle mass, poor muscle quality, or reduced strength. This combination becomes increasingly important with aging because skeletal muscle naturally tends to decline while visceral and total body fat may increase.
The consequences can extend beyond appearance or the number on the scale. Excess adiposity is associated with insulin resistance, inflammation, cardiovascular and metabolic risk, while declining muscle health can contribute to weakness, reduced mobility, lower physical capacity, and loss of independence.
This creates an important challenge in weight management. Aggressive calorie restriction may reduce body fat, but if substantial muscle and strength are also lost, the patient’s body composition and physical function may not improve as much as expected.
For patients with sarcopenic obesity, the objective should therefore be more precise than simply losing weight. Treatment should aim to reduce excess adiposity while preserving or improving skeletal muscle, strength, metabolic health, mobility, and long-term physical function.
Nutrition, adequate protein intake, progressive resistance training, appropriate weight-loss strategies, and monitoring of body composition and physical performance form the foundation of this approach.
7 Powerful Strategies for Sarcopenic Obesity
1. Prioritize Protein to Support Skeletal Muscle
Adequate protein intake is a fundamental component of managing excess body fat while protecting skeletal muscle. This becomes particularly important when calorie intake is reduced for weight loss.
Dietary protein provides essential amino acids needed for muscle protein synthesis. If energy restriction is combined with inadequate protein intake, the risk of losing lean tissue along with body fat may increase.
Protein requirements should be individualized according to age, body size, kidney function, physical activity, baseline muscle mass, nutritional status, and medical history. Older adults may require particular attention because the muscle-building response to dietary protein can become less efficient with aging.
Protein quality and distribution also matter. Consuming high-quality protein across multiple meals can provide repeated opportunities to stimulate muscle protein synthesis rather than concentrating most daily protein in a single meal.
For patients with sarcopenic obesity, adequate protein should therefore be integrated into the weight-loss strategy from the beginning so that reducing excess adiposity does not unnecessarily compromise skeletal muscle.
2. Use Progressive Resistance Training to Build and Preserve Strength
Resistance training is one of the most important interventions for preserving and improving skeletal muscle during weight reduction. Dietary protein supplies the necessary amino acids, while resistance exercise provides the mechanical stimulus that encourages muscle adaptation.
A resistance program may include free weights, machines, resistance bands, or appropriately selected body-weight exercises. The specific approach should be individualized according to age, baseline strength, mobility, orthopedic limitations, cardiovascular status, and previous exercise experience.
Progressive overload is essential. As strength and exercise tolerance improve, resistance, repetitions, training volume, or exercise difficulty should gradually increase so that skeletal muscle continues to receive an adequate stimulus.
Aerobic exercise remains valuable for cardiovascular fitness, insulin sensitivity, energy expenditure, and overall metabolic health. However, aerobic activity alone does not provide the same muscle-building stimulus as appropriately designed resistance training.
For individuals with sarcopenic obesity, combining progressive resistance exercise with adequate protein intake provides a powerful foundation for reducing body fat while maintaining or improving strength, muscle quality, and physical function.
3. Reduce Visceral Fat Without Excessively Rapid Weight Loss
Reducing excess body fat is an important objective in sarcopenic obesity, but the rate and quality of weight loss matter. An aggressive calorie deficit may accelerate weight reduction while also increasing the risk of losing lean tissue.
Visceral fat is particularly important because excess fat surrounding the abdominal organs is associated with insulin resistance, metabolic dysfunction, inflammation, and increased cardiometabolic risk.
The goal should therefore be preferential reduction of excess adiposity while providing enough energy, protein, and essential nutrients to support skeletal muscle and physical activity.
Very rapid weight loss, persistent fatigue, declining strength, reduced exercise performance, or difficulty meeting nutritional requirements may indicate that the energy deficit is too aggressive or that the overall treatment strategy requires reassessment.
For patients with sarcopenic obesity, successful weight management should emphasize improved body composition rather than simply achieving the fastest possible reduction in body weight.
4. Measure Body Composition Instead of Relying Only on BMI
Body mass index is useful for population-level screening, but it cannot distinguish between body fat and skeletal muscle. Two individuals with the same BMI can have substantially different amounts of visceral fat, muscle mass, strength, and metabolic risk.
Body-composition assessment can therefore provide additional information when evaluating patients with excess adiposity and suspected muscle impairment. Methods such as DXA, bioelectrical impedance analysis, and other validated techniques may help estimate fat mass and lean tissue.
These measurements have limitations. Lean mass is not identical to skeletal muscle, and hydration status can influence some methods. Results should therefore be interpreted alongside clinical findings rather than used as a single diagnostic measure.
Waist circumference can provide additional information about abdominal adiposity, while strength and physical-performance testing can help determine whether reduced muscle quantity is accompanied by functional impairment.
For patients with sarcopenic obesity, monitoring changes in fat mass, lean tissue, waist circumference, strength, and physical function provides a more meaningful picture of progress than body weight or BMI alone.
5. Improve Metabolic Health and Insulin Sensitivity
Skeletal muscle is an important site for glucose disposal and plays a major role in metabolic health. Reduced muscle quantity or quality combined with excess adiposity can contribute to impaired insulin sensitivity and abnormal glucose regulation.
Visceral adiposity can further worsen this metabolic environment through increased release of free fatty acids and inflammatory signaling. This helps explain why body composition can be clinically important even when two patients have similar body weights or BMI values.
Resistance training and regular physical activity can improve insulin sensitivity while supporting skeletal muscle. Nutritional strategies that reduce excess energy intake while maintaining adequate protein and nutrient quality can further support improvements in body composition and metabolic health.
Depending on the patient’s medical history, monitoring may include fasting glucose, hemoglobin A1c, lipid levels, blood pressure, waist circumference, and other appropriate cardiometabolic markers.
Managing sarcopenic obesity therefore involves more than reducing body fat. Improving metabolic health while preserving or increasing functional skeletal muscle is an important component of long-term treatment.
6. Address Sleep, Recovery, and Lifestyle Factors
Muscle preservation and fat reduction are influenced by more than nutrition and exercise. Sleep quality, recovery, stress, and daily activity can affect appetite regulation, training performance, glucose metabolism, and the ability to maintain healthy behaviors over time.
Insufficient or disrupted sleep may interfere with recovery and can make weight management more difficult. Sleep disorders such as obstructive sleep apnea are also common among individuals with obesity and may contribute to fatigue, reduced physical activity, and cardiometabolic risk.
Recovery between resistance-training sessions is equally important. Training provides the stimulus for adaptation, but adequate nutrition, sleep, and recovery allow skeletal muscle to respond to that stimulus.
Daily movement should also complement structured exercise. Walking, climbing stairs when appropriate, and reducing prolonged sedentary time can help maintain mobility and overall energy expenditure without replacing dedicated resistance training.
For patients with sarcopenic obesity, integrating sleep, recovery, resistance exercise, nutrition, and regular daily movement creates a more comprehensive strategy for improving body composition and preserving long-term physical function.
7. Track Strength and Physical Function, Not Just Pounds Lost
Successful treatment should produce improvements that extend beyond the scale. Preserving the ability to move, exercise, perform daily activities, and remain physically independent is particularly important as people age.
Strength and physical-performance measurements can provide information that body weight alone cannot. Depending on the individual, useful measures may include grip strength, chair-rise performance, walking speed, balance, resistance-training performance, and the ability to complete normal daily activities.
A patient may lose body weight while simultaneously becoming weaker, which would raise concern about the quality of that weight reduction. Conversely, reductions in body fat accompanied by stable or improving strength can indicate a more favorable change in body composition and physical function.
Tracking resistance-training performance can also be useful. Maintaining or progressively improving strength while body fat decreases provides practical evidence that the nutrition and exercise strategy is supporting functional muscle.
For patients with sarcopenic obesity, the ultimate objective is not simply a lower body weight. It is a healthier body composition accompanied by greater strength, mobility, metabolic health, and long-term physical independence.
How Is Sarcopenic Obesity Identified?
Identifying sarcopenic obesity requires looking beyond body weight and BMI because neither measurement can determine whether excess adiposity is accompanied by impaired muscle strength or reduced muscle quantity.
Clinical assessment may begin with measures of muscle strength and physical function. Grip strength, chair-rise testing, walking performance, and other functional assessments can help identify patients who may have impaired skeletal muscle function.
Body composition can then provide additional information about adiposity and lean tissue. DXA, bioelectrical impedance analysis, waist circumference, and other validated approaches may be useful depending on the clinical setting and available equipment.
Importantly, low measured lean mass alone does not fully characterize sarcopenia. Muscle strength and physical performance provide clinically important information about whether changes in muscle quantity are affecting function.
There is also no single universally adopted diagnostic method for sarcopenic obesity across all populations and clinical settings. Age, sex, ethnicity, body size, measurement technique, and the diagnostic criteria being used can influence classification.
For this reason, evaluation should integrate body composition, muscle strength, physical performance, nutritional status, medical history, and metabolic risk rather than relying on one measurement alone.
Who Is at Greater Risk for Sarcopenic Obesity?
The likelihood of developing sarcopenic obesity generally increases with age, but chronological age alone does not determine risk. Physical inactivity, inadequate nutrition, chronic disease, hormonal changes, and previous periods of significant weight loss can also influence muscle and fat distribution.
Sedentary adults may gradually lose muscle strength and quality while accumulating visceral and total body fat. This combination can develop even when changes in overall body weight appear relatively modest.
Repeated cycles of weight loss and regain may also be relevant, particularly when weight reduction occurs without adequate protein intake or resistance training. If muscle is lost during weight reduction but predominantly fat is regained afterward, body composition may progressively worsen.
Medical conditions that limit mobility or physical activity can further increase risk. Likewise, prolonged illness, hospitalization, inadequate nutritional intake, and medications or conditions that contribute to muscle wasting may require additional clinical attention.
Patients using weight-loss medications who experience substantial or rapid reductions in body weight may also benefit from monitoring muscle health, particularly when they are older or begin treatment with relatively low muscle mass or strength.
Recognizing these risk factors allows sarcopenic obesity to be addressed earlier, when nutritional intervention, resistance training, medical management, and lifestyle modification may help preserve physical function.
What Are the Treatment Goals for Sarcopenic Obesity?
The primary treatment goal is not simply to achieve a lower number on the scale. Effective management should improve the ratio of fat mass to functional skeletal muscle while supporting metabolic health, mobility, and quality of life.
Reducing excess visceral and total body fat remains important because adiposity contributes to insulin resistance and cardiometabolic risk. However, weight reduction should be structured to minimize unnecessary loss of skeletal muscle and strength.
Preserving or improving muscle requires adequate protein and overall nutrition together with progressive resistance exercise. The weight-loss strategy should provide sufficient energy and nutrients to support training, recovery, and normal physiological function.
Treatment goals should also include measurable improvements in physical capacity. Greater strength, improved walking ability, better chair-rise performance, increased exercise tolerance, and easier performance of daily activities may be clinically meaningful even when changes on the scale are modest.
Metabolic markers such as glucose regulation, blood pressure, lipid levels, and waist circumference may provide additional evidence of treatment response.
Ultimately, successful management of sarcopenic obesity means improving body composition and metabolic health while maintaining or increasing strength, mobility, and long-term physical independence.
The Bottom Line on Sarcopenic Obesity
Sarcopenic obesity illustrates why body weight alone is an incomplete measure of health. Excess body fat can coexist with impaired skeletal muscle health, creating a combination that may affect metabolic function, mobility, strength, and long-term independence.
Effective treatment should therefore focus on body composition rather than pursuing weight loss at any cost. Reducing visceral and total body fat is important, but preserving or improving functional skeletal muscle should occur simultaneously.
Adequate protein intake, progressive resistance training, nutrient-dense nutrition, appropriate energy restriction, sufficient recovery, and regular physical activity form the foundation of this approach.
Monitoring should extend beyond the scale. Waist circumference, body composition, muscle strength, exercise performance, metabolic markers, and physical function can provide a more complete picture of whether treatment is producing meaningful health improvements.
This approach becomes particularly important in older adults and in patients undergoing substantial medical weight loss, including those using GLP-1-based therapies, because preservation of muscle and strength should remain an integral part of the treatment strategy.
Ultimately, successful management of sarcopenic obesity means reducing excess adiposity while building or preserving the muscle, strength, metabolic health, and physical capacity needed for healthy aging and long-term independence.
Pingback: Blood Sugar Management Fort Lauderdale: 7 Powerful Strategies
Pingback: Protein Intake During GLP-1 Weight Loss: 7 Proven Tips